Clarithromycin Dosage Calculator for Children
In short: Calculate pediatric clarithromycin doses by weight: 15 mg/kg/day divided every 12 hours, liquid volumes in mL for both suspension strengths, and the 500 mg per-dose and 1 g daily safety caps with warnings. Use the calculator above, then read the guide below to interpret your result and its limitations.
Weight-based pediatric clarithromycin dosing using the FDA-approved label regimen of 15 mg/kg/day divided every 12 hours, with liquid volumes in milliliters and the 500 mg per-dose and 1 g daily safety caps.
This pediatric clarithromycin dosage calculator works out the dose from your child's weight. Enter the weight in kilograms and the suspension strength printed on the bottle (125 mg per 5 mL or 250 mg per 5 mL), and you get the milligrams per dose, the milliliters per dose to measure in the oral syringe, the total milligrams per day, and the mg/kg/day actually achieved. Doses follow the FDA Biaxin label: 7.5 mg/kg every 12 hours (15 mg/kg/day), capped at 500 mg per dose and 1,000 mg per day, with a clear warning whenever a cap binds. The labeled pediatric dosing applies to children 6 months and older; safety under 6 months has not been established.
Calculate the clarithromycin dose
What clarithromycin is and why children take it
Clarithromycin, sold under the brand name Biaxin, is a macrolide antibiotic. It works by binding to the 50S subunit of bacterial ribosomes, the structures bacteria use to build proteins, which stops susceptible bacteria from growing and multiplying. Because it reaches good concentrations in the respiratory tract, ears, and sinuses, pediatricians prescribe it for acute otitis media (middle ear infection) and pharyngitis or tonsillitis caused by susceptible bacteria, and, together with other antimycobacterial drugs, for the treatment or prevention of disseminated Mycobacterium avium complex (MAC) infection in children at risk. It is also one of the macrolides commonly chosen when a child cannot take penicillin, although any history of allergy to clarithromycin or to any other macrolide drug is a contraindication on the FDA label, and a penicillin allergy must be discussed with the prescriber rather than assumed to be fine.
It helps to understand what clarithromycin is not. Like every antibiotic, it has no effect on viruses: it will not shorten a cold, the flu, or most coughs, and giving it for a viral illness only exposes the child to side effects and encourages resistant bacteria. The decision that an infection is bacterial, and that clarithromycin is the right drug for it, belongs to the clinician who examined the child. This page, and the calculator on it, handle only the arithmetic that follows: turning the child's weight into the correct number of milligrams and milliliters once the prescriber has ordered clarithromycin.
Clarithromycin for children is almost always dispensed as a powder that the pharmacist reconstitutes into a liquid suspension, because young children cannot swallow tablets and because a liquid allows the precise weight-based dosing that children need. The two marketed suspension strengths are 125 mg per 5 mL and 250 mg per 5 mL. The calculator asks for the strength because the same milligram dose is a different milliliter volume in each strength, and mixing the two up is one of the most common dosing errors with pediatric liquids.
The label regimen: 15 mg/kg/day divided every 12 hours
The FDA-approved Biaxin label gives a single pediatric regimen for the labeled indications: 15 mg per kg per day, divided every 12 hours, for 10 days. In practice that means each dose is 7.5 mg per kg, given twice a day, roughly 12 hours apart. The label's own pediatric dosage table is calculated on exactly this 7.5 mg per kg every-12-hour basis: a 9 kg child receives 62.5 mg per dose, a 17 kg child 125 mg, a 25 kg child 187.5 mg, and a 33 kg child 250 mg, with the milliliter volumes worked out for each of the two suspension strengths. You can check the calculator against these four label examples. Small differences may appear, because the label table rounds to the most convenient measurable volumes while the calculator keeps the exact weight-based arithmetic, for example the calculator gives a 9 kg child 67.5 mg (2.7 mL of 125 mg/5 mL) where the label table lists 62.5 mg (2.5 mL). Both approaches are within the rounding tolerance of pediatric liquid dosing, but if your prescription label says a different number from the calculator, follow the prescription label and ask the pharmacist about the discrepancy.
The every-12-hour rhythm is not a suggestion. Keeping the two doses roughly 12 hours apart, for example 8 in the morning and 8 in the evening, keeps the drug concentration in the body above the level that inhibits the bacteria for as much of the day as possible. "Twice sometime during the day" with the doses bunched together leaves a long unprotected gap overnight, and a missed or very late dose should be handled the standard way: give it when remembered unless the next dose is nearly due, never double up, and keep the full course going even when the child starts feeling better.
The labeled pediatric dosing applies to children 6 months and older. The FDA label states that the safety and effectiveness of clarithromycin in pediatric patients under 6 months of age have not been established, which is why this calculator's supported weight range starts at 5 kg and why it does not calculate doses for neonates or young infants. Dosing in that age group, if a prescriber considers it, is an individual clinical decision that no general calculator should attempt.
The two caps: 500 mg per dose and 1 g per day
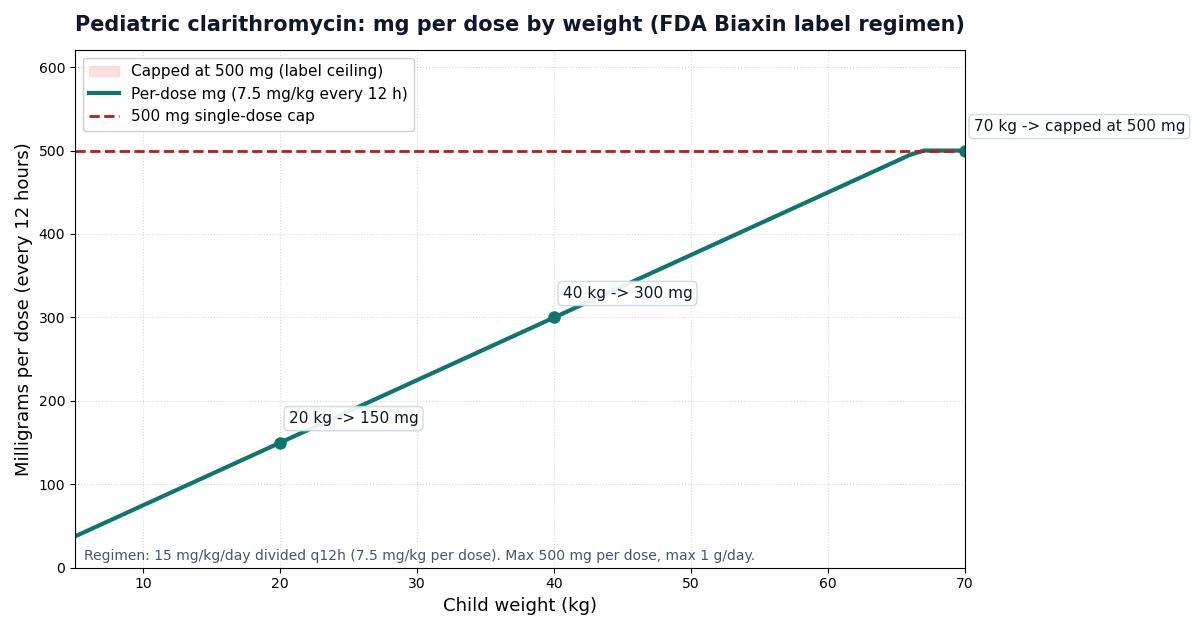
Weight-based dosing has ceilings, and clarithromycin has two of them on the FDA label. No single dose may exceed 500 mg, and the total may not exceed 1 g (1,000 mg) per day. The label phrases this as dosing "up to the adult dose": the standard adult clarithromycin dose is 500 mg every 12 hours, which is 1,000 mg per day, and a child never receives more than an adult. Both caps bind at the same weight, because 7.5 mg per kg times the weight crosses 500 mg at exactly the weight where 15 mg per kg per day crosses 1,000 mg. In this calculator that crossover sits just above 66.7 kg, so a 70 kg child gets 500 mg per dose twice daily for a 1,000 mg total, with warnings that both caps have bound, while a 60 kg child gets the full uncapped arithmetic of 450 mg per dose and 900 mg per day.
A capped dose is a signal, not a suggestion to override the cap. When the calculator shows a cap warning, the weight-based arithmetic wanted more drug than the label allows, which is precisely the situation where the prescriber should double-check the order. Do not "fix" a capped result by switching suspension strengths or rounding up, because neither changes the milligram total. The achieved mg/kg/day shown in the result tells you exactly what the child receives after capping: for a 70 kg child it reads 14.3 mg/kg/day instead of the full 15, which is the documented trade-off the label's ceilings impose at higher weights.
It is worth noting that the 500 mg per-dose ceiling is a pediatric ceiling, not a universal one. For mycobacterial (MAC) infections, the label separately gives 500 mg every 12 hours for adults and 7.5 mg per kg every 12 hours up to 500 mg every 12 hours for pediatric patients, used in combination with other antimycobacterial drugs such as ethambutol. That is a different clinical situation with its own prescribing rules, and the informational duration table below keeps it separate from the standard 10-day courses.
How long the course lasts: duration by indication
The duration of clarithromycin treatment depends on the infection being treated, and the table below is informational only: the prescriber's course length is the one that counts. For the two labeled pediatric indications, acute otitis media and pharyngitis or tonsillitis, the FDA label specifies the 15 mg/kg/day regimen for 10 days. The 10-day figure for streptococcal pharyngitis also matches long-standing treatment guidance, which keeps the 10-day course even when symptoms resolve earlier, because the purpose is to eradicate the bacteria fully, not just to relieve the sore throat.
| Indication | Pediatric regimen (label) | Duration |
|---|---|---|
| Acute otitis media | 15 mg/kg/day divided every 12 hours (max 500 mg/dose, 1 g/day) | 10 days |
| Pharyngitis / tonsillitis | 15 mg/kg/day divided every 12 hours (max 500 mg/dose, 1 g/day) | 10 days |
| MAC treatment or prophylaxis (with other antimycobacterials) | 7.5 mg/kg every 12 hours, up to 500 mg every 12 hours | Longer term: continue while clinical response is observed; stop when the child is at low risk of disseminated infection, per the prescriber |
Finishing the full course matters as much as getting the dose right. Stopping a 10-day course on day 6 because the ear pain is gone leaves the most resistant bacteria alive and invites the infection to return, sometimes in a form that no longer responds to the same antibiotic. If the child is vomiting and cannot keep the medicine down, or shows no improvement within 48 to 72 hours, call the prescriber rather than stopping on your own.
Measuring the suspension accurately
Correct measurement starts at the pharmacy counter: confirm which of the two strengths, 125 mg per 5 mL or 250 mg per 5 mL, is printed on your bottle, and set the calculator to match. A 150 mg dose is 6.0 mL of the 125 mg/5 mL suspension but only 3.0 mL of the 250 mg/5 mL suspension; measuring the 125 mg/5 mL volume from the stronger bottle would give double the intended dose, and the reverse would give half. If the bottle is ever replaced mid-course with the other strength, recalculate the milliliters before giving another dose.
Use the oral syringe supplied with the medicine, never a kitchen spoon. Household teaspoons and tablespoons vary widely in actual volume, and studies of household spoons have repeatedly shown they can deliver anywhere from half to double the intended dose. An oral syringe with milliliter markings removes that guesswork, and the calculator reports the volume to 0.1 mL, which any oral syringe can measure. Shake the bottle well before every dose, because the drug particles settle between doses and an unshaken bottle gives a weak dose from the top and an overly strong dose from the bottom. Measure at eye level on a flat surface, and squirt the liquid slowly toward the inside of the child's cheek rather than the back of the throat, to reduce gagging and spitting out.
The calculator keeps the exact weight-based milligrams (to one decimal place) and reports the milliliter volume to 0.1 mL, which any oral syringe can measure. Store the reconstituted suspension as the label directs, note the discard date printed on the bottle, and do not save leftover suspension for a future illness: it will have expired, and the next illness may need a different drug or dose anyway.
QT prolongation and drug interactions: the safety section to read twice
Clarithromycin has one of the more demanding interaction profiles among commonly used pediatric antibiotics, and this is the section of the label that parents and caregivers should take most seriously. The drug can prolong the QT interval, the electrical recovery phase of the heartbeat, which in susceptible people can degenerate into torsades de pointes, a dangerous ventricular arrhythmia. The label therefore says to avoid clarithromycin in patients with known QT prolongation, in patients taking drugs known to prolong the QT interval, in patients with a history of torsades de pointes, in patients with low potassium or magnesium, in patients with significant bradycardia (slow heart rate), and in patients taking Class IA or Class III antiarrhythmic drugs. Older patients carry a higher risk of torsades, but the warning applies at every age.
On top of the QT warning sits a list of outright contraindications, drugs that must not be combined with clarithromycin at all: cisapride and pimozide, ergot alkaloids (ergotamine, dihydroergotamine), lomitapide, the statins lovastatin and simvastatin, lurasidone, and colchicine in patients with kidney or liver impairment. A history of cholestatic jaundice or liver dysfunction with previous clarithromycin use is also a contraindication, as is hypersensitivity to clarithromycin or any macrolide drug. Beyond these, the label warns that serious adverse reactions can occur from interactions with colchicine, some other lipid-lowering agents, some calcium channel blockers, and other drugs, because clarithromycin raises the blood levels of medicines broken down by the same liver enzyme pathway.
The practical consequence is simple: tell the prescriber about every medicine the child takes, including over-the-counter products and supplements, before clarithromycin is started, and do not start or stop any other medicine during the course without checking. The full interaction list in the label is long, which is why this page summarizes the drug classes and directs you to the label itself rather than pretending a short list is complete. If the child takes a heart medicine, a cholesterol medicine, migraine medicine containing ergotamine, or gout medicine containing colchicine, raise it explicitly with the prescriber or pharmacist.
Two more label safety points deserve a sentence each. Kidney function changes how clarithromycin is cleared: the label directs a dose reduction in severe renal impairment (with or without coexisting liver impairment), either halving the dose or doubling the interval, which is a prescriber decision this calculator does not make. Liver injury is also a labeled warning: stop the drug and seek care if signs of hepatitis appear, such as yellowing of the skin or eyes, dark urine, or persistent abdominal pain. And because the label notes embryo-fetal toxicity in animal studies, clarithromycin is not recommended in pregnancy except where no alternative is appropriate, which matters for adolescent patients.
When clarithromycin is not the right antibiotic
Good antibiotic stewardship is part of safe pediatric care, and it starts with knowing when not to reach for the bottle. Clarithromycin does nothing for colds, flu, most coughs, or any other viral illness, and prescribing data consistently shows that a large share of pediatric antibiotic courses are written for viral infections where they cannot help. Each unnecessary course carries real costs for the child: diarrhea, abdominal pain, nausea, vomiting, and the metallic taste disturbance (dysgeusia) that tops the label's adverse-reaction list for both adults and children, plus the rarer but serious risks of liver injury, dangerous heart rhythm, and Clostridioides difficile-associated diarrhea, which the label warns can range from mild diarrhea to fatal colitis and can appear during or after treatment.
There are also children for whom clarithromycin is the wrong choice even when the infection is bacterial. Babies under 6 months fall outside the labeled pediatric population, as described above. Children with known QT prolongation, certain heart rhythm conditions, or the interacting medicines listed in the previous section need a different antibiotic or a cardiology-aware prescribing decision. Children with severe kidney impairment need prescriber-adjusted dosing, not the standard calculator output. And local resistance patterns matter: in areas where macrolide resistance in the target bacteria is high, guidelines may prefer a different first-line drug, which is another reason the choice of antibiotic is the clinician's call.
The most responsible thing a caregiver can do with this page is to use it exactly as intended: as the arithmetic behind a prescription that a clinician has already written for the right child, the right infection, and the right duration. If any of those three are uncertain, if the child has a heart condition, takes interacting medicines, has kidney or liver problems, or has ever reacted badly to a macrolide, the prescriber or pharmacist should hear about it before the first dose goes in.
What this calculator does and does not do
This calculator converts a child's weight and the bottle's suspension strength into a per-dose amount in milligrams and milliliters, shows the total milligrams per day and the mg/kg/day actually achieved, and enforces the label's 500 mg single-dose and 1,000 mg daily ceilings with visible warnings whenever a cap binds. It keeps the exact weight-based milligrams to one decimal place, and it reports volumes to 0.1 mL.
What it does not do is choose clarithromycin, choose the duration, adjust for kidney or liver impairment, screen for QT risk or drug interactions, or dose children under 6 months. It also does not replace the prescription label: if the label on your bottle says something different from the calculator result, follow the label and ask the pharmacist or prescriber about the discrepancy. A dosing tool supports the prescription; it never overrides it.
Sources
- U.S. Food and Drug Administration. Biaxin (clarithromycin) prescribing information: pediatric patients 15 mg/kg/day divided every 12 hours for 10 days, up to the adult dose (500 mg per dose, 1 g/day); pediatric dosage table calculated on 7.5 mg/kg every 12 hours; suspensions 125 mg/5 mL and 250 mg/5 mL; safety under 6 months not established; QT prolongation warning and contraindications; renal dose adjustment. Available via DailyMed.
- U.S. Food and Drug Administration. Clarithromycin tablets prescribing information (revised 2023): mycobacterial infections, pediatric 7.5 mg/kg up to 500 mg every 12 hours; severe renal impairment dose reduction; adverse reactions including abdominal pain, diarrhea, nausea, vomiting, dysgeusia. Available via DailyMed.
Key takeaways
- The FDA-approved Biaxin label gives 15 mg per kg per day, divided every 12 hours (7.5 mg per kg per dose), for 10 days in pediatric patients, up to the adult dose of 500 mg per dose and 1 g per day.
- For the labeled pediatric indications, acute otitis media and pharyngitis or tonsillitis, the FDA label specifies a 10-day course at 15 mg per kg per day divided every 12 hours.
- The FDA Biaxin label states that the safety and effectiveness of clarithromycin in pediatric patients under 6 months of age have not been established.
- Clarithromycin suspension comes in two strengths: 125 mg per 5 mL and 250 mg per 5 mL.
Frequently asked questions
What is the recommended pediatric dose of clarithromycin?
The FDA-approved Biaxin label gives 15 mg per kg per day, divided every 12 hours (7.5 mg per kg per dose), for 10 days in pediatric patients, up to the adult dose of 500 mg per dose and 1 g per day. The label's pediatric dosage table is calculated on exactly this basis. Confirm the dose with your child's prescriber.
How many days should a child take clarithromycin?
For acute otitis media and pharyngitis or tonsillitis, the label specifies 10 days. For MAC treatment or prophylaxis, the pediatric dose is 7.5 mg per kg every 12 hours up to 500 mg, continued while a clinical response is observed, which is a longer-term prescriber decision. Finish the full prescribed course even if the child feels better early.
Can clarithromycin be given to babies under 6 months old?
The FDA label states that safety and effectiveness under 6 months have not been established. The labeled pediatric dosing applies to children 6 months and older. Any use in a younger infant is an individual prescriber decision, and this calculator does not calculate doses for that group.
How do I measure the clarithromycin liquid dose in mL?
Check whether your bottle is 125 mg per 5 mL or 250 mg per 5 mL, because the milliliter volume differs between the two. Use the supplied oral syringe, shake the bottle well before each dose, and measure to 0.1 mL. Never use a kitchen spoon.
What medicines must not be taken with clarithromycin?
Contraindicated combinations on the label include cisapride, pimozide, ergot alkaloids, lomitapide, lovastatin, simvastatin, lurasidone, and colchicine with kidney or liver impairment. The label also warns against use with known QT prolongation, drugs that prolong the QT interval, Class IA or III antiarrhythmics, and low potassium or magnesium. Tell the prescriber about every medicine the child takes.
What are the common side effects of clarithromycin in children?
The most frequent reactions in trials were abdominal pain, diarrhea, nausea, vomiting, and metallic taste. Serious labeled warnings include liver injury, QT prolongation with dangerous heart rhythm, and Clostridioides difficile-associated diarrhea. Seek care for rash, hives, swelling, breathing difficulty, severe or bloody diarrhea, or no improvement within 48 to 72 hours.
Clinical sources: U.S. Food and Drug Administration, Biaxin (clarithromycin) prescribing information (pediatric dosing 15 mg/kg/day divided every 12 hours for 10 days; pediatric dosage table on 7.5 mg/kg every 12 hours; safety under 6 months not established; QT prolongation warnings and contraindications; via DailyMed).